

"Bioidentical" means the hormone molecule matches what your body already makes; "synthetic" usually means a lab-altered molecule designed to act like a hormone without being identical to it. Neither label tells you whether a product is safe. Safety depends on the specific molecule, the dose, and how it enters your body. FDA-approved bioidentical drugs exist and are well studied; compounded bioidentical preparations mixed at specialty pharmacies are not FDA-approved and carry different, largely unmeasured risks.
TL;DR:
- FDA-approved bioidentical hormones like estradiol patches and micronized progesterone are tested for safety, unlike compounded preparations which lack standardized quality control.
- The route of administration significantly influences risk, with transdermal estrogen lowering clotting risks compared to oral forms, especially when used long-term or at higher doses.
- Major medical organizations, including Mayo Clinic and the Endocrine Society, do not endorse compounded bioidentical hormone therapy over FDA-approved options, citing lack of evidence for safety or effectiveness.
- Personalized hormone therapy should focus on the specific molecule, route, dose, and ongoing lab monitoring rather than marketing labels or vague natural claims.
- Starting hormone treatment within ten years of menopause and maintaining regular oversight reduces risks associated with hormone therapy.
Table of Contents
- Bioidentical vs Synthetic Hormones: The Core Definitions
- The Pharmacology That Actually Changes Your Risk
- What the Evidence and Major Medical Bodies Actually Say
- Compounding, Regulation, and When It's Actually Justified
- Choosing Hormone Therapy: What to Ask Your Prescriber
- How Physician-Supervised Programs Handle Dosing and Monitoring
- The Label Isn't the Decision
- Ready for a Physician-Supervised Plan? Here's Where to Start
- Sources
- FAQ
Bioidentical vs Synthetic Hormones: The Core Definitions
"Bioidentical" describes a hormone with the exact molecular structure your ovaries, testes, or adrenal glands produce naturally, most often estradiol, progesterone, or testosterone. "Synthetic," in the strict pharmacology sense, refers to a molecule engineered to mimic a hormone's effect while differing in structure, like the progestin medroxyprogesterone acetate.
The confusion starts with sourcing. Many bioidentical hormones begin as plant compounds extracted from soy or wild yam, then get chemically converted in a lab into a molecule identical to human estradiol or progesterone. That lab step doesn't make the final product "synthetic" in the way marketers imply. It just means "bioidentical" describes the finished molecule, not the starting plant.
A few things worth remembering when you read a label or a clinic's marketing:
- FDA-approved drugs like estradiol patches, oral micronized progesterone, and many estrogen creams are chemically bioidentical.
- "Compounded" means custom-mixed by a specialty pharmacy rather than manufactured and tested under FDA oversight.
- "Natural" on a package is a marketing word, not a regulatory or chemical category.
The Cleveland Clinic notes that plenty of FDA-approved hormone therapies already contain bioidentical hormones, which undercuts the idea that you need a compounding pharmacy to get a body-identical molecule.
The Pharmacology That Actually Changes Your Risk
The label on the box matters far less than three practical variables: which molecule you're taking, what route delivers it, and how your body processes it. Micronized progesterone and synthetic progestins both raise progesterone-receptor activity, but they don't behave the same way once they're in your bloodstream. Conjugated equine estrogens and bioidentical estradiol both relieve hot flashes, but they metabolize differently through the liver.
Route of administration turns out to be one of the biggest levers you actually control. Oral estrogen passes through the liver first, which increases clotting-factor production. Transdermal estradiol, delivered through a patch or gel, skips that first pass through the liver almost entirely.
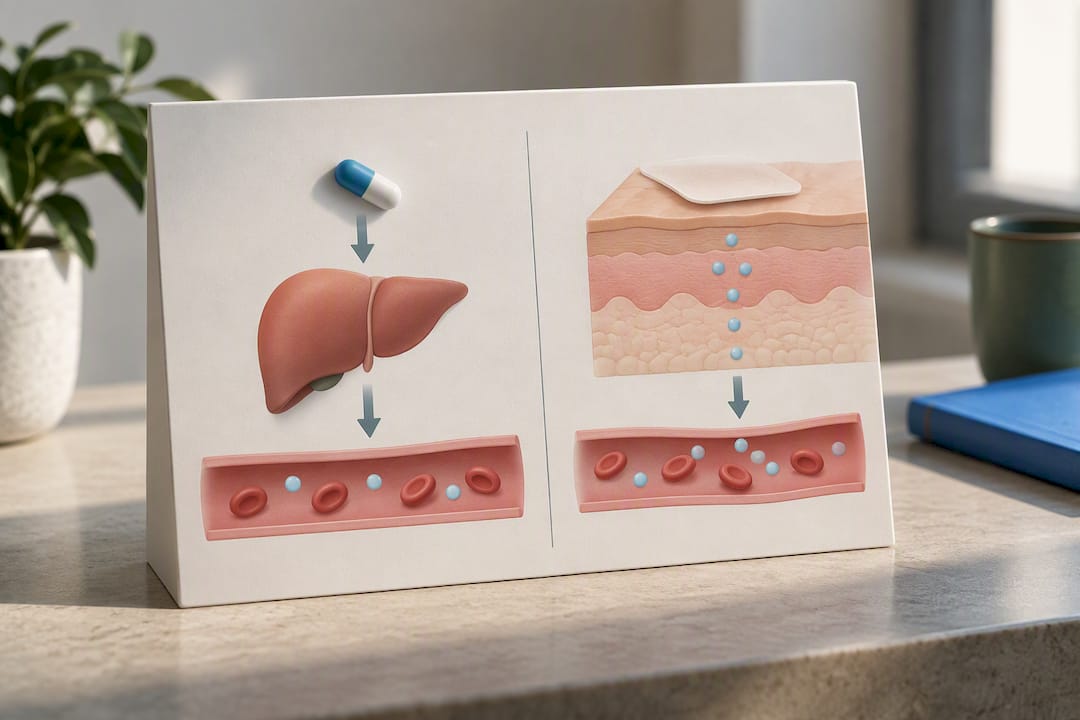
Multiple observational studies point to a meaningfully different risk profile between routes. According to Women's Health Initiative-related analyses, transdermal estradiol has been associated with a lower venous thromboembolism risk than oral estrogen in several cohort studies.
A short list of what actually shifts your risk profile:
- Molecule: micronized progesterone appears to carry a different cardiovascular signal than synthetic progestins in some analyses.
- Route: oral formulations raise clotting-factor synthesis more than transdermal or vaginal delivery.
- Dose and duration: risk in most major trials rises with higher doses and longer continuous use, not short-term or lower-dose regimens.
- Age at initiation: starting hormone therapy closer to menopause onset carries a different risk calculus than starting a decade later.
None of this shows up on a bottle labeled "bioidentical." It shows up in your prescriber's choice of molecule, route, and monitoring schedule, which is exactly why that conversation matters more than the marketing term.
What the Evidence and Major Medical Bodies Actually Say
The Mayo Clinic states plainly that there's no clinical evidence bioidentical hormones are safer or more effective than conventional hormone therapy. That conclusion isn't a dismissal of bioidentical molecules themselves. Plenty of FDA-approved drugs are bioidentical. It's a rejection of the marketing claim that compounded, custom-mixed versions outperform tested, regulated ones.
The Women's Health Initiative, the largest randomized trial on hormone therapy, found that certain older oral estrogen-progestin combinations carried increased risks of blood clots, stroke, and breast cancer in postmenopausal women, particularly with longer use starting well after menopause. Later reanalyses complicated that picture. Timing, formulation, and route all moved the needle.
Synthetic progestins are associated with increased risks of blood clots and stroke in some studies, while observational data on hormone types and cardiovascular risk suggests micronized progesterone may carry a different profile, though the evidence remains largely observational rather than settled by randomized trials.
That distinction, between the original WHI's older synthetic combination and newer data on progesterone versus progestins, is where a lot of "bioidentical is safer" marketing quietly borrows legitimate science and overstates it.
Three things the current evidence actually supports:
- Route (oral vs. transdermal) meaningfully affects clot risk for estrogen therapy.
- Progesterone and synthetic progestins may not carry identical cardiovascular risk, but the data is observational, not conclusive.
- No major medical body, including the Endocrine Society or the National Academies, endorses routine use of compounded bioidentical hormone therapy over FDA-approved alternatives.
The honest summary: some pharmacologic differences are real and worth discussing with a prescriber. "Bioidentical" as a marketing category is not one of them.
Compounding, Regulation, and When It's Actually Justified
FDA approval means a drug went through standardized testing for potency, purity, stability, and dose consistency, and it means the manufacturer reports adverse events under ongoing surveillance. Compounded hormone preparations skip that entire process. A pharmacy mixes a custom dose, often based on saliva testing that lacks validated clinical accuracy, without the batch-to-batch consistency checks that FDA-approved manufacturing requires.
The Mayo Clinic has flagged real potency variability in tested compounded batches, meaning two prescriptions filled at different pharmacies, or even the same pharmacy at different times, can deliver meaningfully different doses of the same "prescription."
There are legitimate reasons to use a compounded hormone:
- A documented allergy to an inactive ingredient (dye, preservative, filler) in every FDA-approved version.
- An unavailable dose or delivery form, such as an ultra-low dose not manufactured commercially.
- A discontinued FDA-approved product with no direct replacement on the market.
Outside those specific situations, routine compounding isn't supported by current clinical guidance from major medical societies.
Pro Tip: If a clinic recommends dosing based only on a saliva hormone test with no blood work and no symptom tracking, treat that as a red flag. Saliva testing hasn't been validated for guiding hormone dosing decisions.
Choosing Hormone Therapy: What to Ask Your Prescriber
Walk into that appointment with your symptoms, goals, and full medical history ready, including any personal or family history of blood clots, stroke, or breast cancer. Age and timing since your last period matter too. Starting therapy within ten years of menopause carries a different risk calculus than starting it well past that window.
Bring these questions:
- Is this specific product FDA-approved, or is it compounded?
- Why this molecule and this route, rather than an alternative?
- What benefits should I realistically expect, and by when?
- What are my personal risk factors for clots, stroke, or breast cancer with this option?
- What's the monitoring plan, including labs and follow-up visits?
| Decision factor | What to confirm with your prescriber |
|---|---|
| Product status | FDA-approved formulation vs. compounded preparation |
| Route | Oral, transdermal, vaginal, or injectable, and why |
| Personal risk | History of VTE, stroke, or hormone-sensitive cancer |
| Monitoring | Baseline labs, symptom check-ins, follow-up schedule |
| Duration | Planned length of use and reassessment timing |
Compounding may be reasonable if you've documented an allergy or need a dose form that isn't commercially manufactured. Outside that, an FDA-approved bioidentical or synthetic option, chosen for your specific risk profile, is the better-supported starting point.
How Physician-Supervised Programs Handle Dosing and Monitoring
Getting the molecule and route right is only half the equation. The other half is tracking how your body actually responds over time, which is where supervised programs earn their value. Airmedfit structures its hormone replacement therapy around baseline lab work, physician review, and scheduled follow-up rather than a one-time prescription handed over without a plan.
That approach looks like:
- Lab panels before treatment starts, to establish your actual hormone levels rather than guess.
- A physician-reviewed plan based on your specific labs, symptoms, and risk factors.
- Ongoing monitoring visits to adjust dose or route if your labs or symptoms shift.
If you're weighing estrogen against progesterone formulations or wondering how a physician-supervised TRT program actually tracks results, those specifics matter more than whichever label sits on the packaging.
The Label Isn't the Decision
"Bioidentical" tells you something real about chemistry. It tells you nothing about whether a specific product, at a specific dose, through a specific route, is right for you. That's the gap a lot of marketing exploits, and it's the gap a good prescriber closes.
The more useful question isn't "bioidentical or synthetic." It's "which molecule, which route, which dose, and who's watching my labs six months from now." Patients who ask that second question tend to get better, safer outcomes than patients who simply ask for "the natural one."
— Organic
Ready for a Physician-Supervised Plan? Here's Where to Start
Certain hormone therapy services build treatment plans around lab data and physician oversight instead of a guessed dose or a saliva-test shortcut. These programs emphasize starting with actual bloodwork rather than marketing language about what's "natural."

The path is straightforward. You start with a doctor's consultation, either async or live, where a physician reviews your symptoms and history. From there, a lab panel, tailored to men's or women's essential markers, establishes your actual baseline instead of relying on guesswork. That data feeds into a personalized plan under the Signature HRT or TRT Membership, which includes ongoing physician supervision and follow-up labs to adjust dosing as your body responds.
This route fits those seeking an evidence-based starting point rather than a compounded product sold on marketing alone.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Bioidentical hormones: Are they safer? - Mayo Clinic
- Observational/WHI-related analyses on hormone types and cardiovascular risk - PubMed
- Bioidentical Hormones: Therapy, Uses, Safety & Side Effects - Cleveland Clinic
FAQ
Why don't doctors prescribe compounded bioidentical hormones more often?
Most major medical bodies, including Mayo Clinic, don't recommend routine compounded bioidentical hormone therapy because it lacks FDA approval and the safety-testing data that comes with it. Doctors generally prefer FDA-approved bioidentical or synthetic options with established dosing and monitoring guidelines, reserving compounding for documented allergies or unavailable dose forms.
What are the downsides of bioidentical hormones?
The molecule itself isn't inherently risky, but compounded bioidentical products carry potency variability, since testing has found inconsistent dosing across batches. They also lack the standardized adverse-event reporting that FDA-approved drugs require, which makes long-term safety harder to track.
What's the safest form of hormone therapy?
There's no single "safest" form for everyone. The evidence points to transdermal estradiol carrying a lower clot risk than oral estrogen in several studies, and micronized progesterone showing a different cardiovascular signal than synthetic progestins in observational data. The right choice depends on your personal risk factors, which is why a physician-reviewed plan, like the ones built through Airmedfit's HRT membership, starts with your labs rather than a generic recommendation.
Do you age faster without hormone therapy?
Declining estrogen and testosterone during menopause or andropause do contribute to changes like bone density loss and shifts in skin elasticity, but "aging faster" isn't a clinical measure hormone therapy is designed to reverse. Hormone therapy is prescribed to manage specific symptoms and documented risk factors, not as an anti-aging treatment, and that distinction matters when a clinic frames it otherwise.